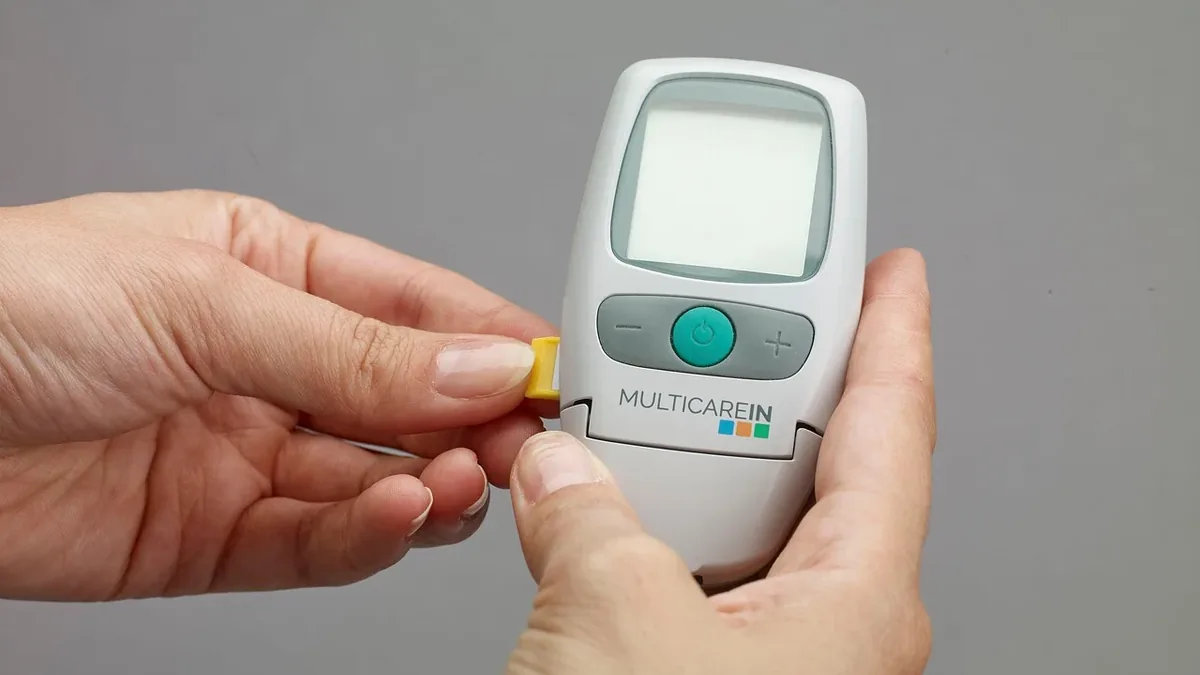
Diabetes
| Country of origin | United States |
|---|---|
| First created | 1960s |
| Original use | Companion cat |
| Size | Medium |
| Coat | Short, plush, dense |
| Shedding | Low to moderate |
| Temperament | Affectionate, gentle, quiet |
| Good with children | Yes |
Origin and history
Diabetes mellitus is not a modern condition but has been documented for millennia. Ancient Egyptian manuscripts from the Ebers Papyrus, circa 1500 BCE, describe symptoms consistent with excessive urination and weight loss. Greek physician Aretaeus of Cappadocia is credited with coining the term "diabetes" in the 2nd century CE, deriving it from a Greek word meaning "to pass through." Early medical understanding was limited to symptom observation, with the sweet taste of urine noted by physicians in ancient India and later by Thomas Willis in the 17th century. The pivotal distinction between Type 1 and Type 2 diabetes was not established until the early 20th century, following the discovery of insulin in 1921. Its historical prevalence spans all human populations, though its recognition as a distinct metabolic disorder evolved over centuries.
What it was bred for
Diabetes is not bred for a purpose; it is a chronic metabolic disorder arising from complex interactions between genetics and environment. In the context of evolution, some genetic predispositions linked to Type 2 diabetes may have conferred survival advantages in historical periods of feast and famine, a concept known as the "thrifty genotype" hypothesis. The condition itself results from the body's inability to properly produce or utilize insulin, the hormone responsible for regulating blood glucose levels. This dysfunction leads to elevated blood sugar, which, if unmanaged, causes systemic damage. Unlike a selectively bred trait, diabetes is an unintended consequence of physiological mechanisms failing under specific pressures. Its increasing prevalence in modern times is largely attributed to sedentary lifestyles and dietary patterns, rather than any designed function.
Life cycle
The life cycle of diabetes refers to its natural history and progression within an individual if left unmanaged. It typically begins with a prediabetic state, characterized by insulin resistance and slightly elevated blood glucose levels. Without intervention, this often progresses to overt Type 2 diabetes, marked by chronic hyperglycemia. Over years and decades, persistently high blood sugar damages small and large blood vessels, leading to the development of complications. These complications include neuropathy, retinopathy, nephropathy, and increased risk of cardiovascular events. The final stages of the condition involve managing these often debilitating complications, which can significantly reduce quality of life and life expectancy. The cycle can be altered at any stage through lifestyle modification and medical treatment, though some damage may be irreversible.
Character and appearance
Diabetes has no singular physical appearance, as it is an internal metabolic state. Its "character" is defined by its clinical signs, symptoms, and long-term effects on the body. Common early symptoms include excessive thirst (polydipsia), frequent urination (polyuria), unexplained weight loss, and persistent fatigue. In advanced or poorly controlled cases, physical manifestations of complications may become visible, such as slow-healing skin ulcers or changes in the retina observable through ophthalmoscopy. Acanthosis nigricans, a darkening and thickening of the skin in body folds, can be a visible marker of insulin resistance. The condition's true "appearance," however, is primarily seen in diagnostic metrics like elevated fasting blood glucose or HbA1c levels, not in a uniform external phenotype.
Pros and cons
There are no advantages or "pros" to having diabetes; it is a detrimental health condition. A significant con is the relentless, daily self-management burden involving glucose monitoring, medication, dietary calculation, and exercise planning. Common regrets among those diagnosed often stem from earlier lifestyle choices, though genetic factors play a substantial and sometimes unavoidable role. A frequent mistake is underestimating the condition's seriousness, leading to inconsistent management and "burnout" from the constant vigilance required. What genuinely goes wrong is the insidious onset of complications, which can develop silently over years before manifesting as vision loss, kidney failure, or nerve pain. Another major con is the substantial financial and emotional cost of lifelong treatment and monitoring, which can create significant stress for individuals and families.
Who it suits
Diabetes suits no one; it is an undesirable condition. This section instead outlines the profiles of individuals at highest risk. Type 2 diabetes often suits those with a strong genetic predisposition, particularly in certain ethnic groups including those of South Asian, African-Caribbean, and Hispanic descent. It is more likely to develop in individuals with a sedentary lifestyle, excess body weight (especially abdominal obesity), and a diet high in processed foods and sugars. A history of gestational diabetes or conditions like polycystic ovary syndrome also increases suitability for developing the disorder. Importantly, while these factors increase risk, diabetes can and does occur in individuals outside these profiles, including those of seemingly healthy weight. Ultimately, no one is ideally suited for diabetes, and prevention through modifiable lifestyle factors is the primary goal for at-risk populations.